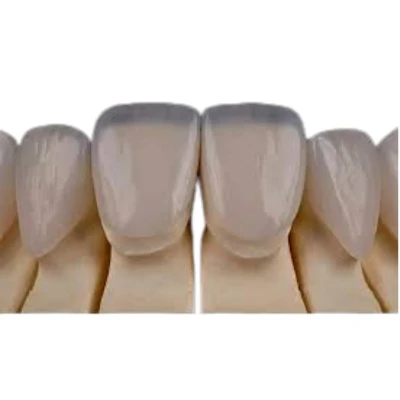






Porcelain veneers demand precision. As a digital dental laboratory that processes thousands of veneer cases each year, we see the direct impact of preparation decisions on fit, esthetics, and longevity. Small errors in reduction, margin design, or planning force adjustments in the lab-thicker layers, color mismatches, or remakes. The goal here is simple: outline the most frequent preparation mistakes we encounter and explain how to avoid them for predictable results.
Veneer preparation means controlled removal of enamel (and sometimes dentin) to create space for the restoration while preserving as much natural tooth structure as possible. Standard guidelines call for facial reduction of 0.3–0.7 mm depending on the area, incisal reduction of 1.0–1.5 mm (or up to 2.0 mm for heavy functional cases), and margins in enamel whenever feasible. Deviations from these ranges lead to the issues listed below.

Key Principles of Veneer Preparation
Before diving into mistakes, here are the core rules we rely on in the lab:
- Aim for uniform space to match porcelain thickness (typically 0.4–0.7 mm facial, thicker at incisal for translucency).
- Keep most reduction in enamel for optimal bond strength.
- Use depth guides and diagnostic tools to plan ahead.
- Consider occlusion, soft tissue, and the full smile display (often 8–10 teeth visible).
Different prep levels suit different goals:
|
Prep Type |
Facial Reduction |
Incisal Reduction |
Typical Use Case |
Risk if Misapplied |
|
No-prep / Minimal |
0–0.5 mm |
0–1.0 mm |
Minor color/shape changes |
Bulky look if under-reduced |
|
Moderate |
0.5–0.8 mm |
1.0–1.5 mm |
Standard esthetic cases |
Sensitivity if over-reduced |
|
Aggressive |
0.8–1.5 mm |
1.5–2.0 mm |
Major changes, discoloration |
Weak bond, fracture risk |
Start with a diagnostic wax-up or mock-up. It serves as the blueprint for reduction and provisional fabrication.

Top Common Mistakes in Veneer Preparation
These are the errors we see most often when cases arrive at our lab.
1. Failure to Address Gingival Symmetry First
Gingival heights set the foundation for esthetics. Centrals should sit 1–2 mm more apical than laterals, with canines level or slightly lower. Uneven gingiva forces uneven veneer lengths or margins that look off.
Consequence: Final smile appears asymmetrical even with perfect veneers.
Fix: Evaluate and correct symmetry early-via orthodontics, laser gingivectomy, or crown lengthening. Discuss this during treatment planning.
2. Skipping Diagnostic Wax-Up or Mock-Up
Without a wax-up, preparation happens blind. No visual guide for final contours, incisal edge position, or occlusion.
Consequence: Veneers end up bulky, short, or misaligned with soft tissue.
Fix: Always fabricate a wax-up. Use it to make reduction guides, practice on a model, and create provisionals that test esthetics and phonetics.
3. Over-Preparation
Removing too much enamel exposes dentin, weakens bond, and increases sensitivity.
Consequence: Thin porcelain in spots prone to fracture; patient discomfort.
Fix: Use depth-cutting burs (0.3 mm gingival, 0.5 mm middle, 0.7 mm incisal thirds). Verify with reduction guides and dental microscope for precision.
4. Under-Preparation or Uneven Reduction
Insufficient or inconsistent space leads to overcontoured veneers.
Consequence: Thick appearance, plaque traps, gingival irritation, and stress fractures from thin porcelain layers.
Fix: Place depth grooves first. Blend them carefully. Check uniformity from multiple angles.
5. Poor Margin Design and Placement
Feather-edge margins confuse lab technicians. Deep subgingival margins harm periodontium and complicate impressions.
Consequence: Overcontouring to hide margins, microleakage, or inflammation.
Fix: Use 0.3–0.5 mm chamfer or shallow shoulder margins at or slightly above the gingival crest. Keep them clear and in enamel.
6. Inadequate Incisal and Proximal Reduction
Cut less than 1.5 mm incisal or skip proximal extension.
Consequence: Thin porcelain in load-bearing areas cracks; diastemas fail to close properly.
Fix: Reduce incisal to 1.5–2.0 mm with butt-joint design. Extend proximally as needed for natural contours. Follow the 4-8-10 rule-treat teeth visible in full smile.
7. Ignoring Occlusal Factors
Prep focuses only on facial without checking centric stops or excursions.
Consequence: Porcelain overload in function leads to chipping.
Fix: Analyze occlusion pre-prep. Adjust for anterior guidance. For bruxers, consider stronger materials like lithium disilicate and slightly deeper reduction.
8. Sharp Angles, Undercuts, or Steps
Leaving rough transitions or undercuts.
Consequence: Stress concentrations cause fractures; lab struggles with fit.
Fix: Round all line angles. Use fine-grit burs for smooth finish. Inspect from different views.
9. Inadequate Tissue Management and Provisionals
Poor retraction causes bleeding in impressions. Skipping provisionals skips functional testing.
Consequence: Margin errors, sensitivity, or mismatched final veneers.
Fix: Use aluminum chloride hemostatics. Always place provisionals to evaluate esthetics, occlusion, and phonetics.
10. Poor Communication and Impression Quality
Missing shade maps, photos, or detailed notes. Single imperfect impression.
Consequence: Color mismatches, adaptation issues.
Fix: Send two full-arch impressions (digital preferred). Include pre-op photos, stump shades, and patient expectations.
These mistakes often overlap. One small oversight compounds others.
Tools and Best Practices for Precision
To minimize errors:
- Depth-cutting burs and silicone reduction guides.
- Dental microscope for uniform control.
- Digital scanners for accurate capture.
- Pre-prep CBCT if root or bone concerns exist.
Communicate early with the lab. Upload prep scans, photos, and wax-up details. Good data lets us flag issues before fabrication.
Real-World Examples
We recently received a case with under-reduced incisal edges (less than 1.0 mm) and uneven facial reduction. The veneers came back bulky in the middle third, requiring remake. Another case skipped wax-up-final veneers mismatched gingival levels, leading to patient dissatisfaction.
In contrast, cases with depth guides, mock-ups, and clear communication fit seamlessly on first try, with natural translucency and no adjustments needed.
Final Thoughts
Veneer preparation is technique-sensitive. Millimeters decide whether the restoration looks natural, bonds reliably, and lasts. Avoid these common pitfalls by planning thoroughly, using guides, and verifying every step.
ADS Dental Laboratory Ltd specializes in providing high-precision CAD/CAM veneers to overseas clinicians. We are one of the largest veneer factories in China, with a very professional team dedicated to veneers. We can produce Feldspathic veneer, Emax veneer, Zirconia veneer, and Composite veneer.
Send us your prep scans or photos-we provide feedback to catch issues early and deliver consistent, custom restorations that reduce remakes.
Ready to discuss your next case? Contact us.